














Our Guide to Understanding Fertility Issues
- How common are fertility difficulties?
- When should I seek help?
- Why is it difficult for some people to get pregnant?
- What is metabolic disturbance?
- Medical treatment for reduced insulin sensitivity and metabolic conditions
- What about natural supplements for reduced insulin sensitivity?
- Can general multivitamins help undiagnosed fertility problems?
- Summary
How common are fertility difficulties?
They are fairly common, affecting about 1 in 6 couples. The age at which you start trying for a baby can be very significant: the chances of getting pregnant begin to decline rapidly by the late 30s. At age 38-39, 3 women in 10 will not conceive after 12 months of trying.
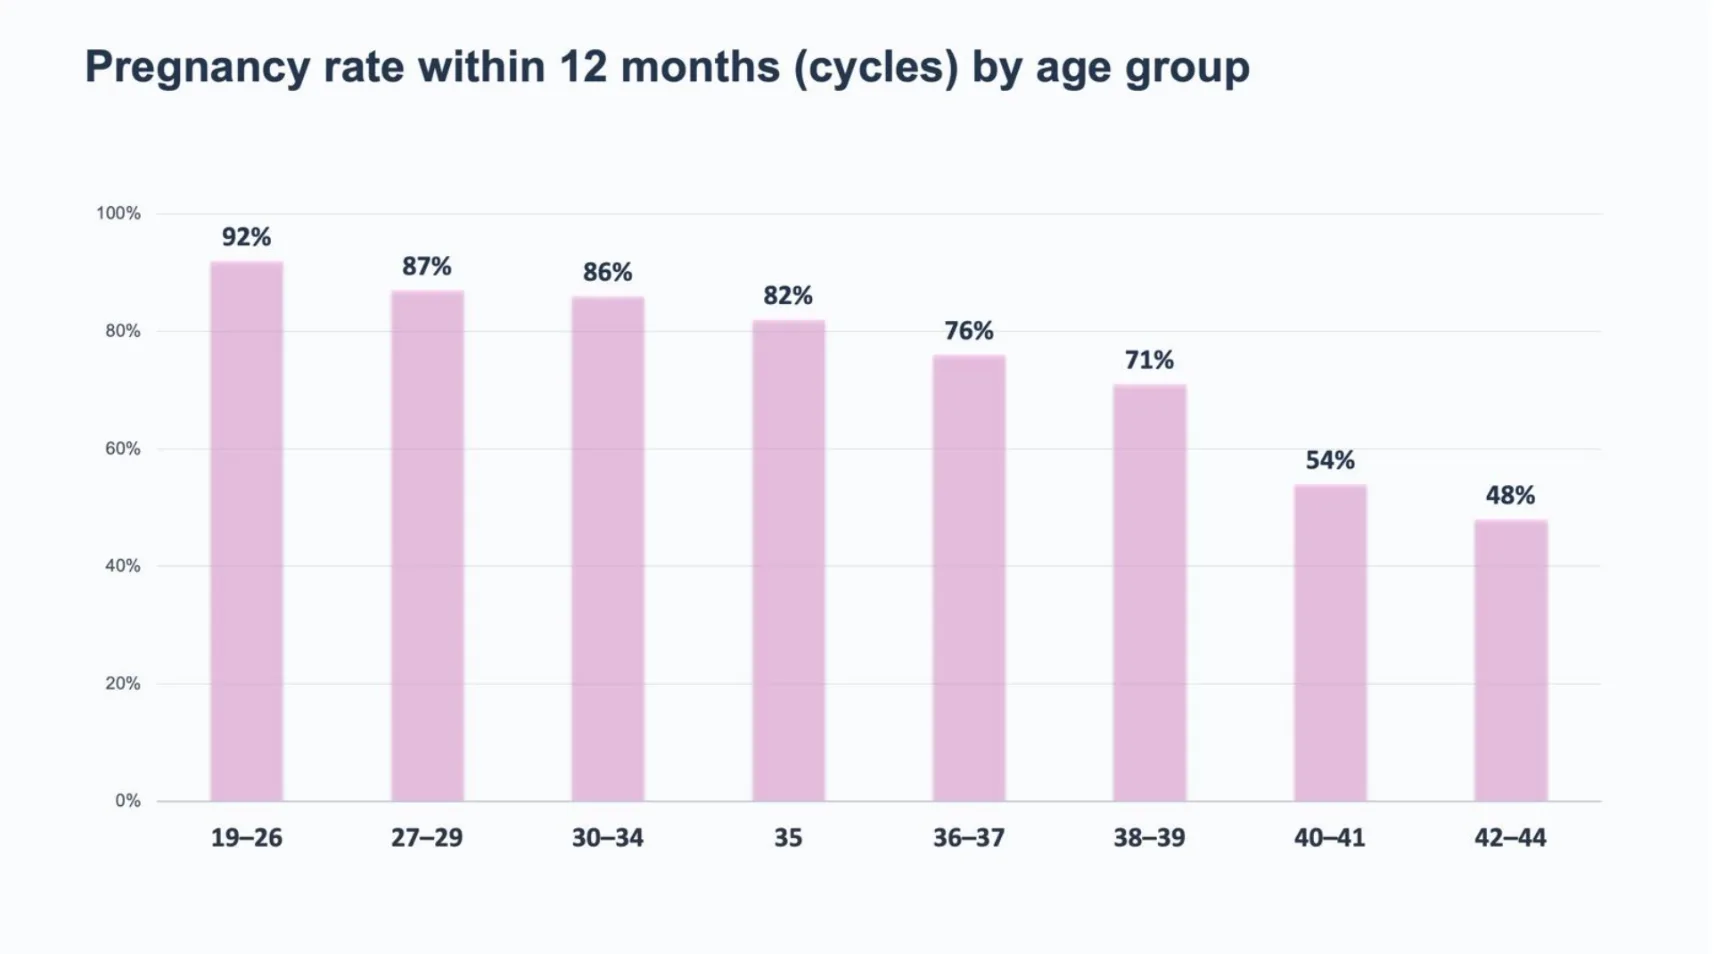
National Health Service England; Steiner et al. Fertil Steril. 2016 Mar 5;105(6):1584–1588.
Wesselink et al. American Journal of Obstetrics and Gynecology. 2017 Dec;217(6):667.e1-667.e8.
When should I seek help?
Many women who take longer than a year to get pregnant will still go on to conceive. But the NHS suggests that it may be helpful to seek medical advice after a year of trying, and sooner for anyone aged 36 and over or who is already aware they may have fertility problems.
A fertility assessment can help identify the possible underlying causes that are making it difficult to get pregnant. You may need further investigations or treatment. However, current tests cannot find all the causes of fertility problems. In these cases, a fertility specialist can provide further advice and develop a management plan tailored for you.
Why is it difficult for some people to get pregnant?
Many different factors can affect the chances of getting pregnant. These can relate to the female reproductive system, the male reproductive system, or both partners. They include age, the quality of eggs and sperm, ovulation, the timing of intercourse, weight, smoking and alcohol use, as well as other underlying reproductive conditions.
In this section we look at some common factors affecting female fertility, grouped into three categories:
- those that can be identified and treated,
- those that can be identified but cannot be treated, and
- those where no clear cause can be identified.
Problems that can be identified and treated
Some fertility problems have a relatively clear diagnosis and an established treatment. Examples include:
- problems with ovulation, including some forms of polyendocrine metabolic ovarian syndrome (PMOS), formerly known as polycystic ovary syndrome (PCOS)
- significant thyroid or prolactin abnormalities
- blocked fallopian tubes
- significant male factor infertility
- some abnormalities of the uterus, such as polyps or certain fibroids that may affect fertility.
Depending on the cause, treatment may include medicines to help ovulation, treatment of hormonal conditions, surgery, or fertility treatments such as IVF.
Problems that can be identified but can’t easily be treated
Sometimes a biological factor causing fertility problems can be found, but there may be limited options for treating it. Age-related changes in egg quality and a reduced number of eggs remaining in the ovaries (the ovarian reserve) are important examples.
Tests such as AMH, antral follicle count and FSH can help assess ovarian reserve, but no treatment is available to alter the number of eggs. And there is currently no established treatment that can reliably reverse age-related changes in the chromosomes of eggs.
Problems that may be difficult to identify
Sometimes fertility tests do not find a clear reason why a couple is having difficulty conceiving. This is known as unexplained infertility or subfertility. It does not mean that there is no underlying biological cause. Rather, it means that current tests have not found one that can be reliably treated.
In women, researchers are investigating several factors that may play a part, including:
- subtle changes in metabolism or hormones
- changes in how the fallopian tubes work
- changes in the lining of the womb (endometrium)
- inflammation and the way the immune system responds
- changes in the micro-organisms that naturally live in the reproductive system, known as the reproductive microbiome.
Some of these changes can be detected using specialised or experimental tests. However, there is still much to learn. In many cases, researchers do not yet know whether a particular change is contributing to fertility difficulties, or whether treating it can improve the chances of having a baby.
Subtle metabolic and hormonal changes are relatively common among these possible factors. The next section looks more closely at these.
What is metabolic disturbance?
Metabolic disturbance is a broad term for changes in the way the body processes and uses energy. These changes can affect how the body controls blood sugar, processes and stores fats, manages inflammation and produces hormones.
Many factors can play a part, including genetics, excess fat around the internal organs, diet, lack of physical activity, poor sleep, long-term stress, ageing and certain hormone-related conditions. Together, these factors can affect the body’s normal metabolic balance and functioning.
What is insulin resistance or reduced insulin sensitivity?
Reduced insulin sensitivity is one type of metabolic problem. Insulin is a hormone that helps the body use glucose from the blood for energy. With reduced insulin resistance the body's cells do not respond to insulin as well as they should. The body may then produce more insulin to compensate, leading to higher levels of insulin in the blood. Insulin resistance is a term that describe relatively heavy reduction in insulin sensitivity. Over time, insulin resistance can affect the body’s ability to control blood sugar and fats and may contribute to fatty liver disease and chronic low-level inflammation.
The changes can also influence one another. For example, excess fat and inflammation can make insulin resistance worse, while insulin resistance can contribute to further metabolic changes. This can create a cycle that becomes harder for the body to manage over time.

Ohgi et al. Fertility and Sterility. 2008 Aug;90(2):373-7.
De Ugarte et al. Fertility and Sterility. 2005 May; 83(5):1454-1460.
Albert et al. Human Reproduction. 2025;40(8):1562-1574. doi:10.1093/humrep/deaf100
Insulin resistance is common in women with PMOS and can also occur in women without PMOS. Estimates for insulin resistance in women without PMOS vary from about one in ten to about four in ten women. Many people with insulin resistance or reduced insulin sensitivity go undiagnosed as their symptoms are not always obvious and testing is not carried out routinely.
How reduced insulin sensitivity can affect fertility
Insulin resistance can be one of several factors affecting fertility in women with metabolic problems, particularly those with PMOS. It can also occur in women with prediabetes or type 2 diabetes and is more common in some women who are overweight or have other metabolic risk factors.
When the body becomes less responsive to insulin, it may produce more insulin to keep blood sugar under control. Higher insulin levels can encourage the ovaries to produce more androgen hormones, such as testosterone, and affect the balance of reproductive hormones in the body.
These hormonal changes can interfere with the growth and development of ovarian follicles, which are the sacs containing developing eggs. They can also affect ovulation when a mature egg is released from the ovary. For some women, this may make it more difficult to get pregnant.
Reduced insulin sensitivity may affect fertility in other ways too. Research suggests that it may influence egg health by affecting how cells produce energy and respond to oxidative stress. Oxidative stress happens when harmful molecules called free radicals build up faster than the body can control them, which can damage cells. Reduced insulin sensitivity may also affect the development of the lining of the womb and how well prepared it is for an embryo to implant.
However, reduced insulin sensitivity is only one part of a much bigger picture. As we have explained, the chances of becoming pregnant are influenced by many factors, including age, the quality of eggs, sperm and embryos, the timing of intercourse and diet, sleep, alcohol use and smoking. The effect of reduced insulin sensitivity will therefore vary from one woman to another, and it should not be considered the sole cause of difficulties with fertilisation, implantation or pregnancy.
What can I do for reduced insulin sensitivity?
One of the most effective ways to improve insulin sensitivity is to support your overall metabolic health. There are several positive steps that may help:
- being regularly physically active, including both aerobic exercise and strength training,
- working towards a healthy weight,
- eating a healthy balanced diet that you can sustain over time,
- getting enough good-quality sleep and seeking help for sleep problems,
- avoiding smoking, and
- keeping alcohol intake withing recommended limits.
For women with obesity and PMOS, even a relatively modest weight loss may improve the body’s response to insulin and support more regular ovulation. Lifestyle changes are one part of managing insulin resistance. Medical treatments and supplements may also be considered in some circumstances. We look at these in the next section.
Medical treatment for reduced insulin sensitivity and metabolic conditions
Medical treatment will depend on what is contributing to a woman's fertility difficulties. For women with reduced insulin sensitivity or metabolic problems, this may involve treating the underlying condition, supporting ovulation or using fertility treatments such as IVF.
Metformin and weight loss drugs
Metformin is a medicine that improves the body’s response to insulin and may help some women with PMOS. However, it can cause side effects and the evidence that metformin alone increases the chance of a live birth is limited.
Weight management medicines may substantially improve metabolic health for some people. They may improve insulin sensitivity. However, some are not suitable when trying to conceive or during pregnancy, so it is important to discuss their use with your doctor when planning a pregnancy.
Letrozole for supporting ovulation
For women with PMOS who do not ovulate regularly, a medicine called letrozole can be used to stimulate ovulation. It is often the first treatment offered to women with PMOS who are having difficulty becoming pregnant because of problems with ovulation.
IVF
IVF may be recommended when other treatments have not been successful or when there are other fertility problems. Medicines are used to stimulate several eggs to develop in the ovaries. The eggs are then collected and fertilised with sperm in a laboratory, before an embryo is transferred into the womb.
IVF can help some women whose fertility difficulties are associated with insulin resistance, but it does not work on insulin sensitivity itself. The chances of success depend on many individual factors.
Summary – medical treatment for people with reduced insulin sensitivity
Overall, treating conditions such as PMOS, prediabetes and type 2 diabetes can support metabolic and reproductive health. However, reduced insulin sensitivity is only one of many factors that can affect fertility, and it is still unclear how much treating reduced insulin sensitivity on its own improves the chances of having a baby.
What about natural supplements for reduced insulin sensitivity?
Several supplements and natural ingredients have been studied for their ability to improve insulin sensitivity and fertility, particularly in women with PMOS. Some have shown promising results, although the strength of the evidence varies.
When looking at research, it is important to distinguish between improvements in metabolic or hormonal health and improvements in fertility. A supplement may improve measures such as insulin sensitivity or hormone levels without necessarily increasing the chances of becoming pregnant or having a baby.
D-chiro-inositol and myo-inositol
D-chiro-inositol and myo-inositol (DCI-MI) are two forms of inositol that have often been studied for their effect on fertility challenges, particularly in women with PMOS. They are naturally occurring forms of sugar in the body that have a role in the effectiveness of insulin.
There are early evidence that a combination of DCI and MI in a specific dose can improve some metabolic and hormonal imbalances. The effects include imbalances related to reduced insulin sensitivity. Early research also suggests potential benefits for egg maturation and the chances of pregnancy and live birth, although further research is needed.
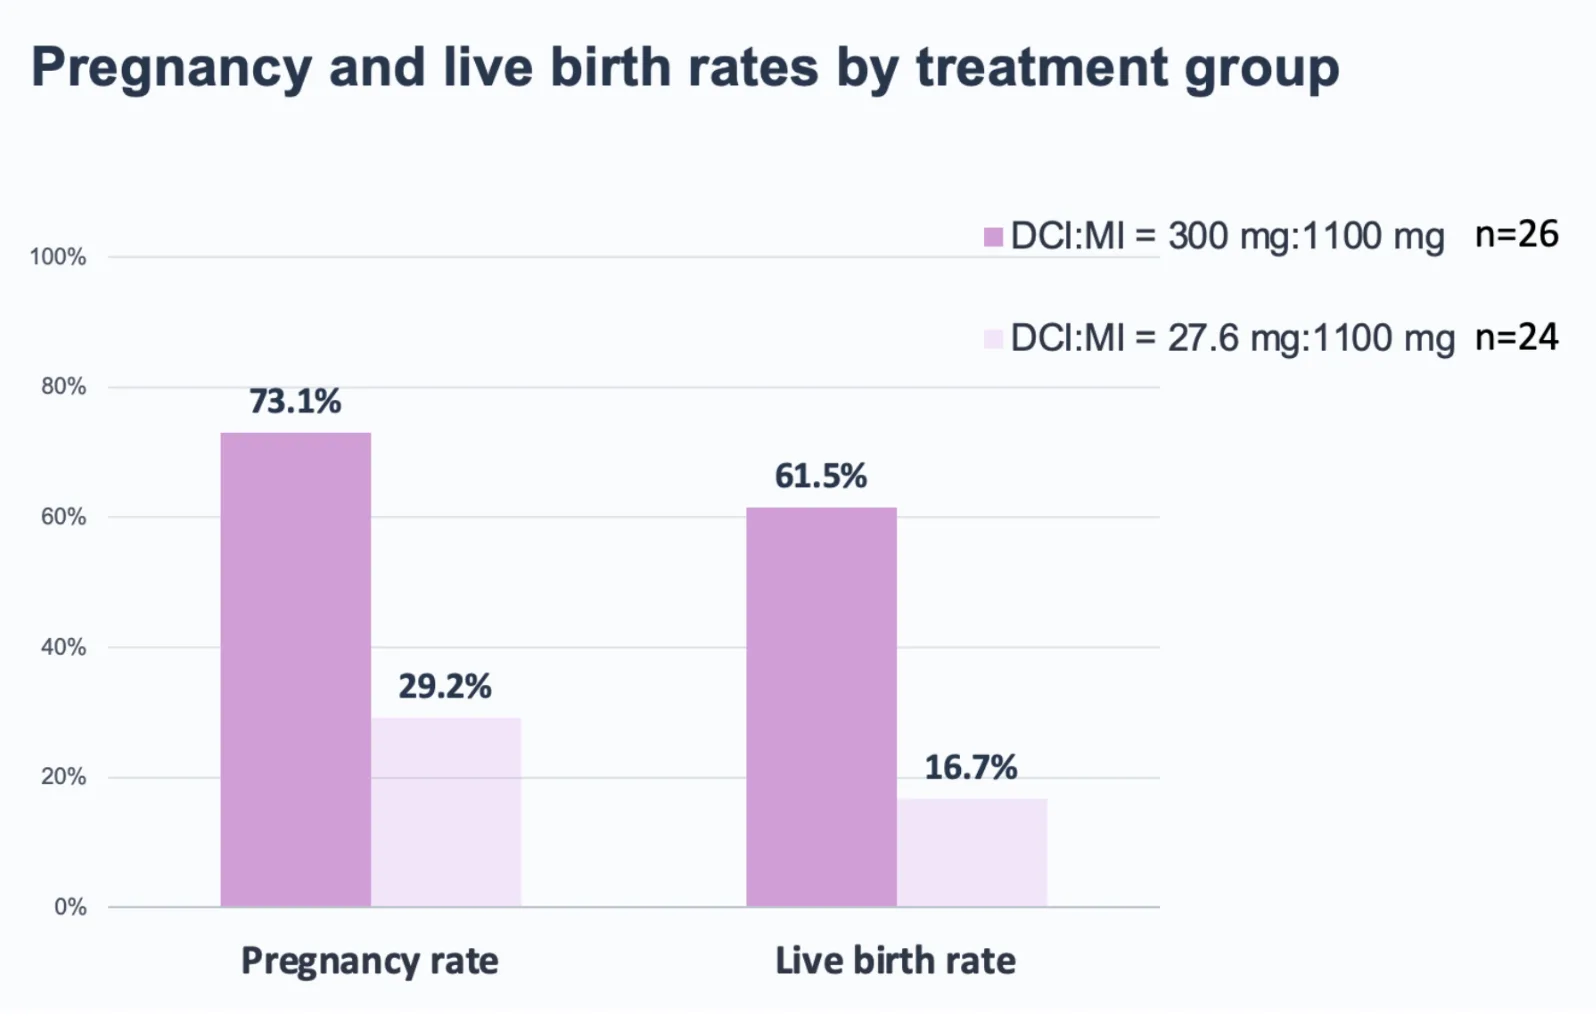
Source: Mendoza et al. Gynaecological Endocrinology, 2019, vol. 35, No. 8, 695-700
Myo-inositol
Myo-inositol alone is also commonly used on its own by women with PMOS and may help improve some symptoms and metabolic measures. However, the evidence that myo-inositol alone increases the chance of pregnancy or live birth is inconsistent.
Berberine
Berberine has been studied for its potential effects on reduced insulin sensitivity, metabolism and hormone levels in women with PMOS. Some findings have been promising, but results have been inconsistent. There is currently not enough evidence for improving the chances of a live birth.
Curcumin, Omega-3, cinnamon and other supplements
Curcumin, Omega-3, cinnamon and several other supplements have also been studied for their possible effects on reduced insulin sensitivity and metabolic health. Some research has produced promising findings, but there is not yet enough evidence to consider these as established treatments for improving fertility.
Summary – supplements for people with reduced insulin sensitivity
Some supplements may improve the way the body responds to insulin or other measures of metabolic health, but this does not necessarily mean they will improve the chances of becoming pregnant or having a baby.
Of the supplements discussed here, the combination of D-chiro-inositol and myo-inositol in a specific formula has some evidence of potential fertility benefits, particularly in women with PMOS. It may therefore be worth considering as a supportive option for women whose fertility difficulties are linked to reduced insulin sensitivity although further research is needed.
If you are trying to conceive or having fertility treatment, speak to a healthcare professional before taking a new supplement. They can help you decide whether it is appropriate for you and how it might fit alongside any other treatment you are receiving.
Can general multivitamins help undiagnosed fertility problems?
Vitamins and minerals are important for overall health and a healthy pregnancy, but there is limited evidence that taking a general multivitamin substantially improves fertility in couples trying to conceive naturally unless there is specific deficiency. If you are having difficulty becoming pregnant, it is important to seek advice about possible causes rather than relying on supplements alone
Recommend Products
Palomacare®
Price range: £16.95 through £46.80 (VAT included)
 Shop Now
Ovosicare® Fertility
- 60 capsules - £39.90 (£0.67 per capsule)
- 180 capsules - £114.10 (£0.63 per capsule)
Price range: £39.90 through £114.10 (VAT included)
 Shop Now

Social
Sign up to receive our newsletter and a welcome discount code:
Disclaimer: Information on this website is provided for informational purposes only and not intended as a substitute for the advice provided by your physician or other healthcare professional. You should not use the information on this website for diagnosing or treating a health problem or disease, or prescribing any medication or other treatment. For medical advice, diagnosis and prescription, please consult a healthcare professional. More Information >
Disclaimer: Information on this website is provided for informational purposes only and not intended as a substitute for the advice provided by your physician or other healthcare professional. You should not use the information on this website for diagnosing or treating a health problem or disease, or prescribing any medication or other treatment. For medical advice, diagnosis and prescription, please consult a healthcare professional.
© LivBio Limited 2024 All Rights Reserved.
